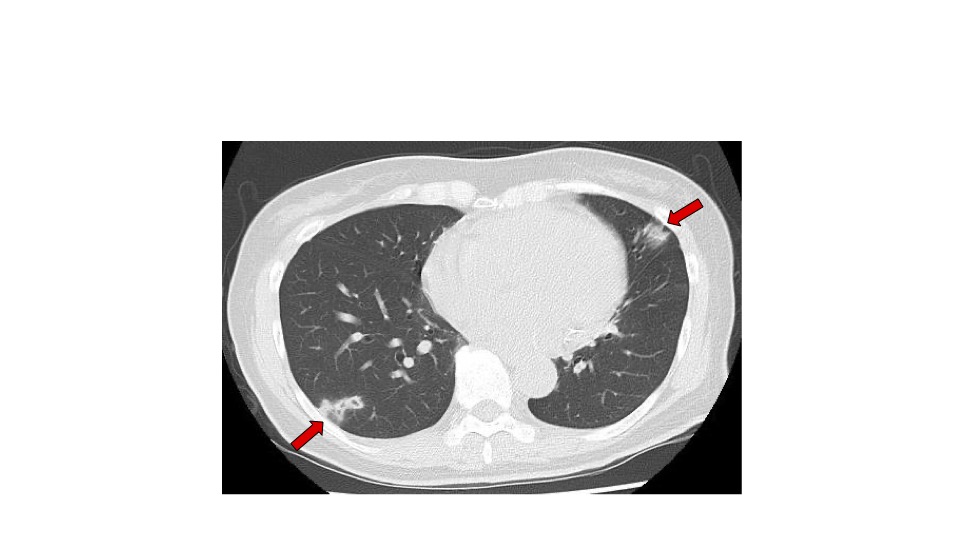
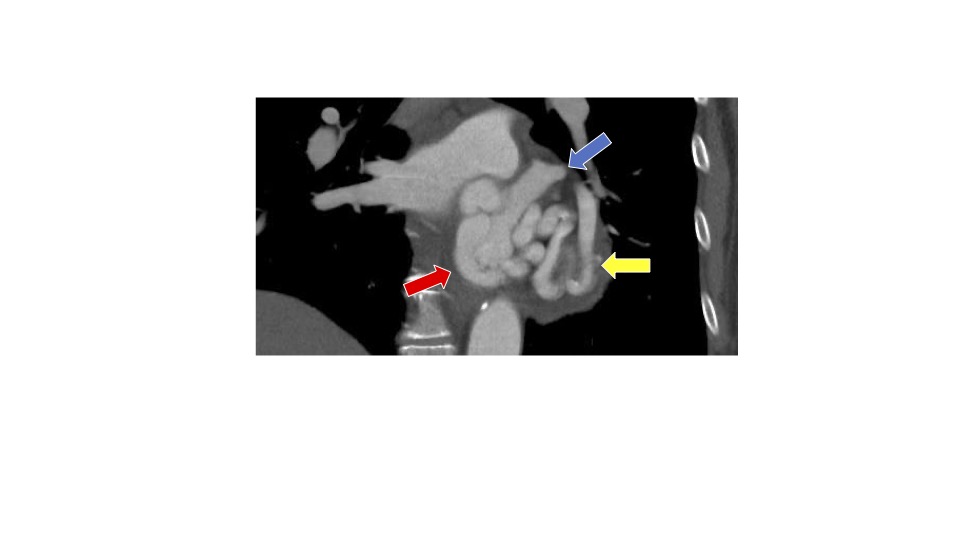
Case Presentation: A 59-year-old woman with hypertension and dyslipidemia presented with one month of appetite loss, a 5-kg unintentional weight loss, and a week of night sweats. Several days before the onset of appetite loss, she had undergone a tooth extraction for a periapical abscess. On presentation, she was afebrile, hemodynamically stable, and without murmurs. Laboratory tests showed a white blood cell count of 12,000/μL and an elevated C-reactive protein level of 65 mg/L. Contrast-enhanced chest CT demonstrated multiple small cavitating nodules in bilateral lower lung lobes (Fig. 1), consistent with septic pulmonary emboli. No dental infection or systemic abscess was identified. The following day, two sets of blood cultures grew Streptococcus gordonii. In the context of the recent dental procedure, multiple septic pulmonary emboli, and S. gordonii bacteremia, the hospital medicine team considered infective endocarditis (IE) highly probable. Transthoracic and transesophageal echocardiography (TEE) showed no valvular vegetations but revealed dilation of both coronary ostia and an abnormal blood vessel running along the left atrial wall. Coronary CT angiography and invasive coronary angiography confirmed a coronary arteriovenous fistula (CAF) originating from the right coronary artery and the left circumflex artery and draining into the coronary sinus (Fig. 2). Intravenous ceftriaxone produced rapid clinical improvement. In light of this favorable response, multidisciplinary discussion among hospital medicine, cardiology, and cardiothoracic surgery supported conservative management for this admission, without surgical intervention on the CAF. On day 24, antibiotic therapy was switched to oral amoxicillin–clavulanate, but it was discontinued three days later because of a severe drug eruption. Given her relatively young age and the associated risk of recurrent IE, she was referred to cardiothoracic surgery for surgical evaluation.
Discussion: CAFs are rare congenital coronary anomalies in which coronary arteries establish aberrant connections with low-pressure structures such as the cardiac chambers, the coronary sinus, or the pulmonary artery. They are often detected incidentally and are frequently asymptomatic in adults. Despite the absence of vegetations on TEE, S. gordonii bacteremia and septic pulmonary emboli met criteria for “possible IE” under the current guidelines. The inpatient team’s stepwise approach—early suspicion of IE, prompt echocardiography, and escalation to advanced coronary imaging—enabled identification of an occult CAF that explained the patient’s septic pulmonary emboli and informed management. CAFs may lead to serious complications, including myocardial ischemia, heart failure, and IE. Therefore, hospitalists should maintain vigilance for concealed structural lesions such as CAFs when evaluating suspected IE, even in the absence of valvular vegetations. Recognition of CAFs can redirect management, including consideration of surgical closure and counseling regarding prophylactic antibiotics before dental procedures.
Conclusions: When IE is strongly suspected but valvular abnormalities are not detected on echocardiography, hospitalists should consider occult structural disease and employ multimodality imaging to refine diagnosis and management.