Background: Bedside procedure services (BPS) have emerged in hospital medicine to address delays in common procedures such as paracentesis, thoracentesis, and lumbar puncture. These services aim to improve operational efficiency, reduce reliance on interventional radiology, and enhance patient-centered care. Reported benefits include shorter time-to-procedure, reduced hospital length of stay (LOS), improved patient satisfaction, and increased educational opportunities for trainees. Prior studies suggest that delays in procedures, particularly paracentesis for suspected spontaneous bacterial peritonitis, are associated with worse outcomes. Timely bedside procedures may mitigate these risks. Despite growing adoption, data on the impact of BPS on LOS remain limited. Our study evaluated whether implementing a hospitalist-led bedside procedure service was associated with a reduction in hospital LOS.
Methods: BPS was introduced at our institution in February 2022 as 7 days a week daytime hours service. Procedures not performed by the BPS continued to be performed by the primary team, specialty consult services or interventional radiology. We included adult inpatients, age >18, admitted to a medicine service under inpatient status who underwent paracentesis, thoracentesis, or lumbar puncture February 2022 and January 2023. Transplant patients and patients who received > 1 of the same type of procedure were excluded as time to procedure was unlikely to impact LOS. The primary outcome was Average LOS (ALOS). Patients with ALOS greater than 90 days were excluded. Welch’s t-test was used to compare mean LOS between BPS and non-BPS procedures.
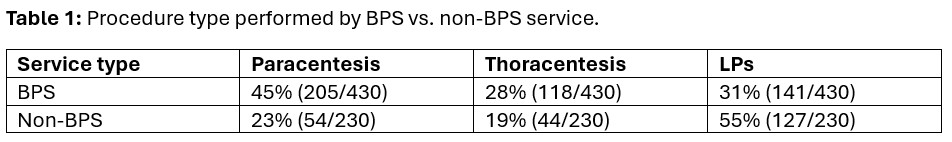
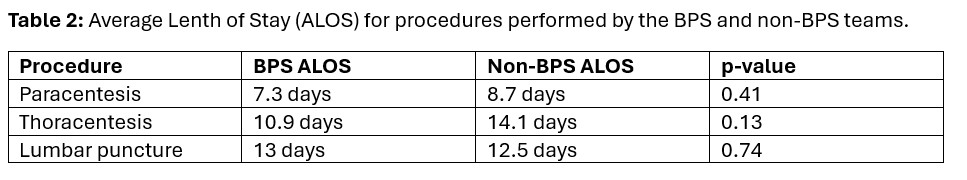
Results: Three patients (ALOS 190, 103 days and 90 days) were excluded from BPS dataset while no patients were excluded from non-BPS data set. A total of 459 procedures were performed by BPS, and 230 procedures were performed by non-BPS teams. BPS performed more paracentesis (45%, 205/430), while non-BPS teams performed more lumbar punctures (55%, 127/230) (table 1). The ALOS for BPS patients was 9.9 days, while the ALOS for non-BPS patients was 11.9 days (p-value 0.06). ALOS for each procedure type is provided in table 2.
Conclusions: Although the adjusted median LOS decreased by 2.0 days, this difference did not reach statistical significance (p = 0.06). The trend suggests meaningful potential clinical benefit, as even modest LOS reductions can improve patient flow and reduce costs. The lack of significance may reflect limited power and residual confounding inherent to retrospective designs. Matching patients across time periods was challenging because other time limited LOS interventions, case mix, and illness severity can bias results. A meta-analysis showed limited data with heterogenous studies supporting the impact of a BPS on LOS. Our next steps include further statistical analyses to adjust for comorbid conditions and baseline characteristics so we may add to the evolving data supporting inpatient bedside procedure services.