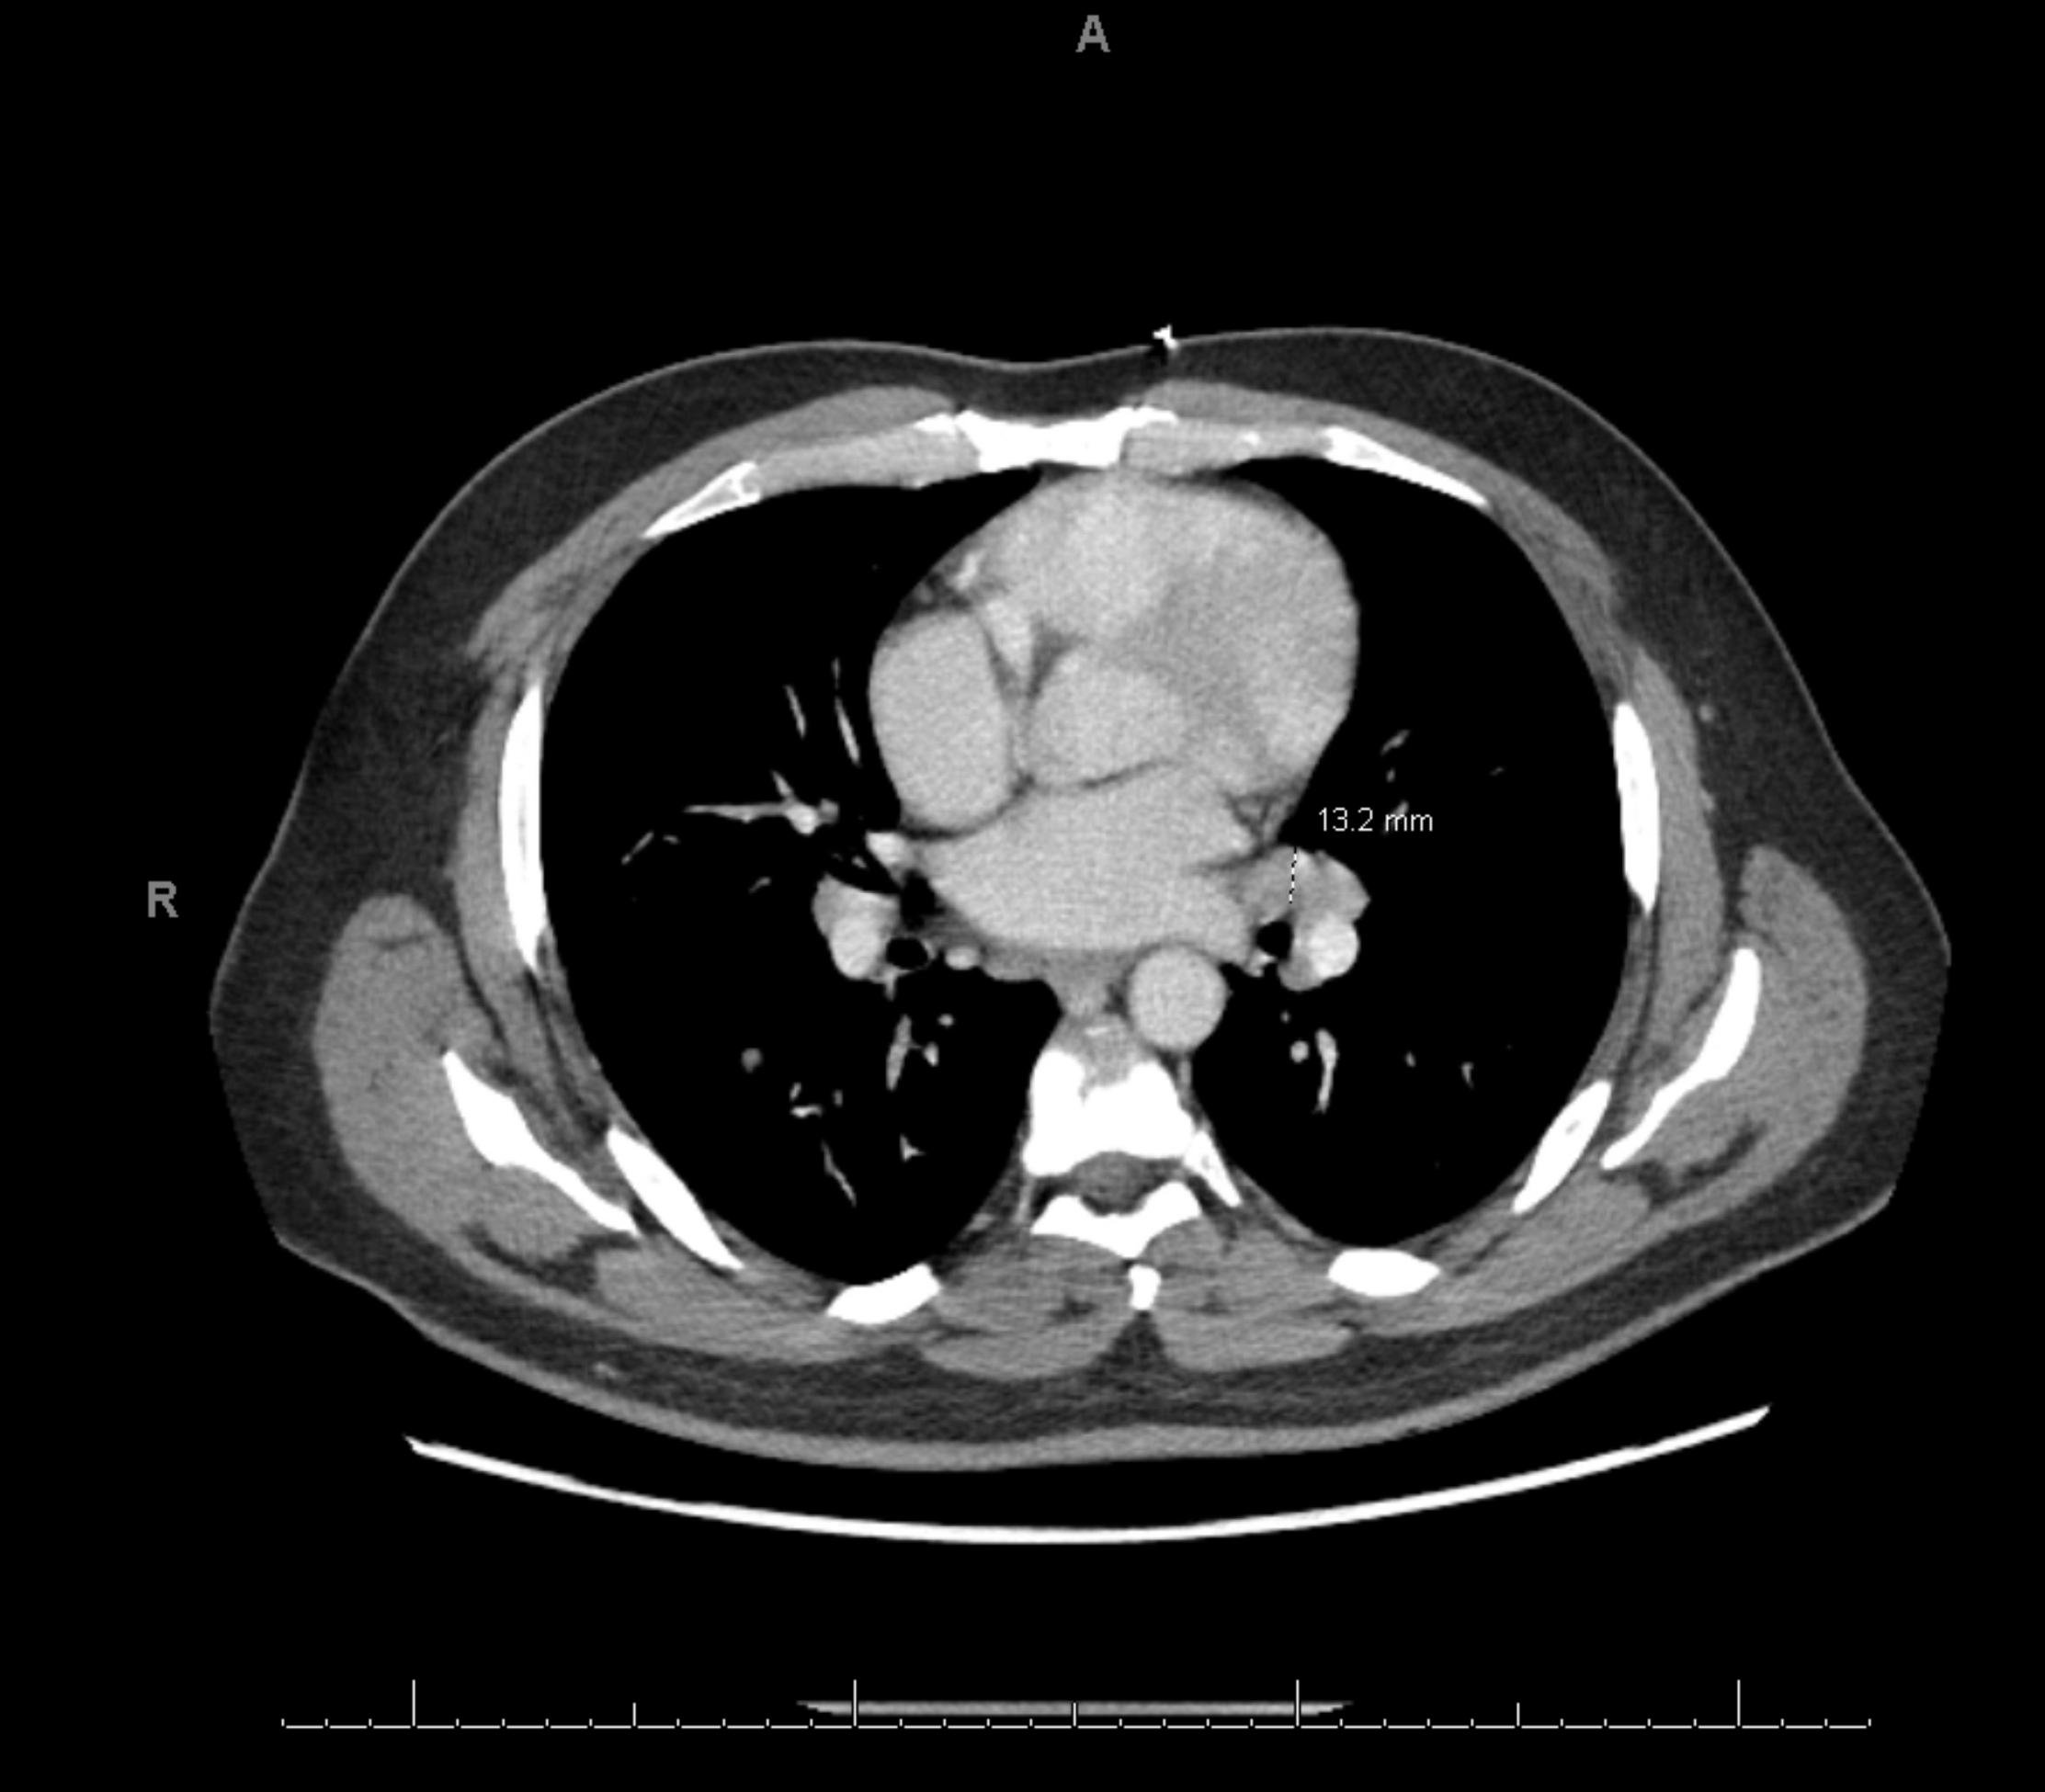
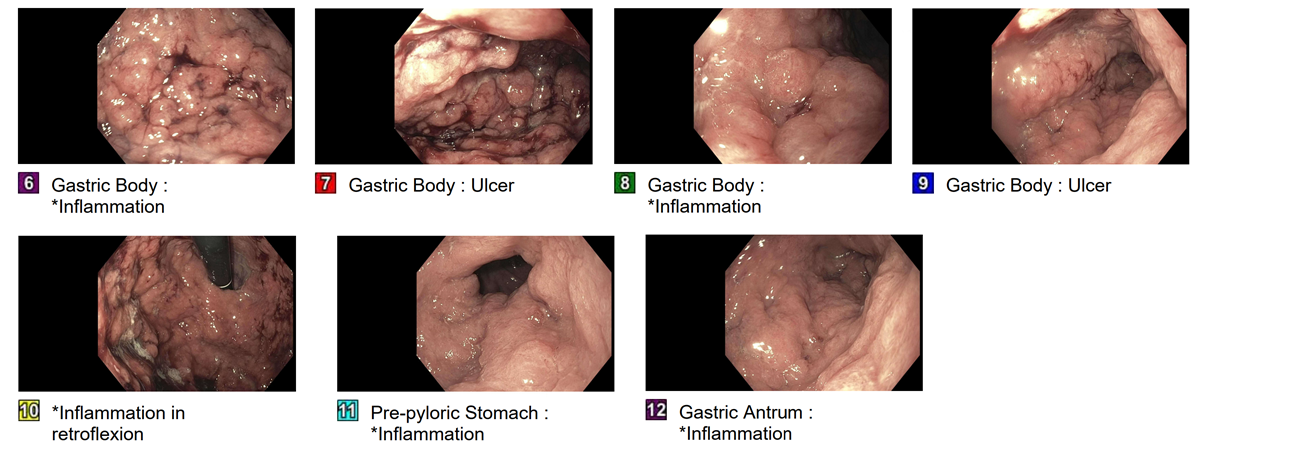
Case Presentation: A 36-year-old African American male presented with 3 weeks of epigastric pain radiating to the left lower back, decreased appetite, unintentional weight loss, occasional acid reflux, and nausea with daily episodes of dark, non-bloody emesis. He reported social alcohol use but otherwise denied any other substance use, medications, or supplements. He had no family history of malignancy or inflammatory bowel disease (IBD). On physical exam, he was in no acute distress, hemodynamically stable, with nondistended, non-tender abdomen, no palpable lymphadenopathy (LAD), and no active signs of bleeding. Lab work was notable for a normal hemoglobin and platelet count with a mean corpuscular volume of 78.8 fL, white blood cell count of 11.5 x 10³/µL, lipase of 446 units/L, aspartate aminotransferase of 41 units/L, alanine aminotransferase of 89 units/L, and negative viral hepatitis panel. Patient was seen 1 week prior for the same presentation with computed tomography (CT) of the abdomen showing diffuse gastric wall thickening, and he was discharged with a diagnosis of gastritis. Repeat CT abdomen revealed worsening thickening and LAD without evidence of pancreatitis. Pulmonary nodules were present and subsequent CT of the chest showed a perivascular distribution with mild diffuse thoracic LAD. Endoscopic Gastroduodenoscopy (EGD) showed diffusely severe active gastritis. Biopsy was notable for numerous granulomas. There was no evidence of malignancy or IBD. Workup for H. pylori, T. whipplei, CMV, HSV, EBV, Cryptococcal and Bartonella species, and TB was negative. Serologies for HIV and syphilis were negative. Biopsy of the pulmonary nodules revealed noncaseating granulomas consistent with sarcoidosis, further evidenced by ANA positivity. He was started on prednisone and a proton-pump inhibitor, with resolution of his symptoms and pulmonary nodules on follow-up 2 months later.
Discussion: Sarcoidosis is a chronic multisystem granulomatous disorder with an estimated national prevalence of 60 per 100,000. Gastric sarcoidosis is a rare extrapulmonary manifestation, occurring in 0.1 to 0.9% of patients with sarcoidosis. Though uncommon, a review of 305 case reports found up to 22% of these cases were life-threatening due to complications such as GI hemorrhage, obstruction, and perforation. Early recognition and treatment are essential to prevent progression and reduce morbidity. As demonstrated by our patient’s rapidly worsening gastritis, urgent EGD and biopsy are warranted in symptomatic patients.Maintaining a broad differential is critical to avoid misdiagnosis and guide appropriate management. Importantly, EGD findings such as gastric infiltration and ulceration are nonspecific. Diagnosis hinges on biopsy showing noncaseating granulomas, in contrast to the caseating granulomas of infectious etiologies. Gastric sarcoidosis may mimic IBD, drug-induced gastritis, systemic vasculitis, amyloidosis, gastric malignancy, and lymphoma. Our patient’s pulmonary findings and serologies supported a systemic process. Further workup and careful biopsy interpretation are key in differentiating granulomatous diseases with overlapping histology.
Conclusions: Gastric sarcoidosis remains an underrecognized entity, often presenting with nonspecific symptoms that overlap with more common gastrointestinal disorders. This case underscores the importance of maintaining a broad differential and need for biopsy when evaluating gastritis with atypical imaging features.