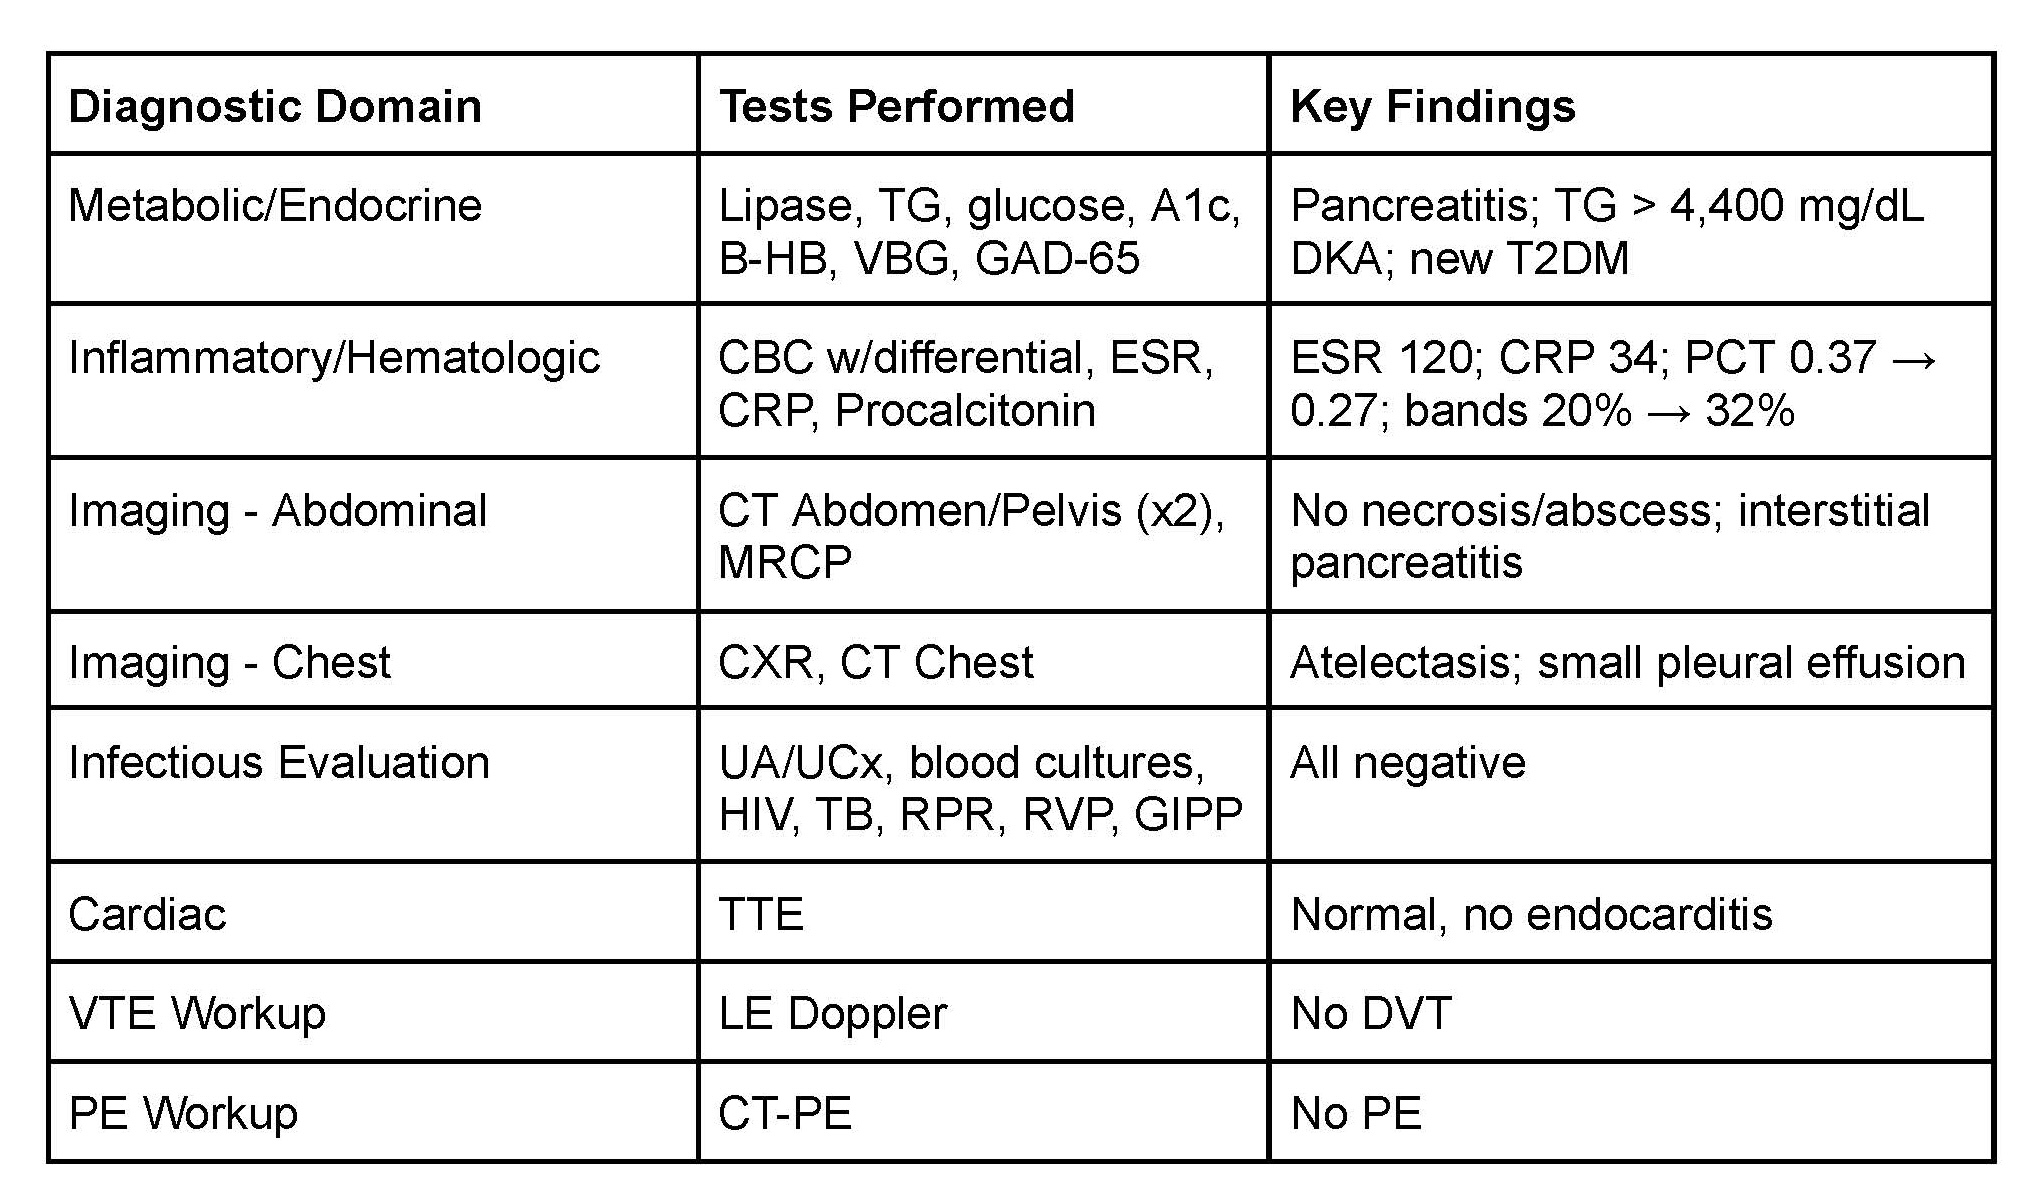
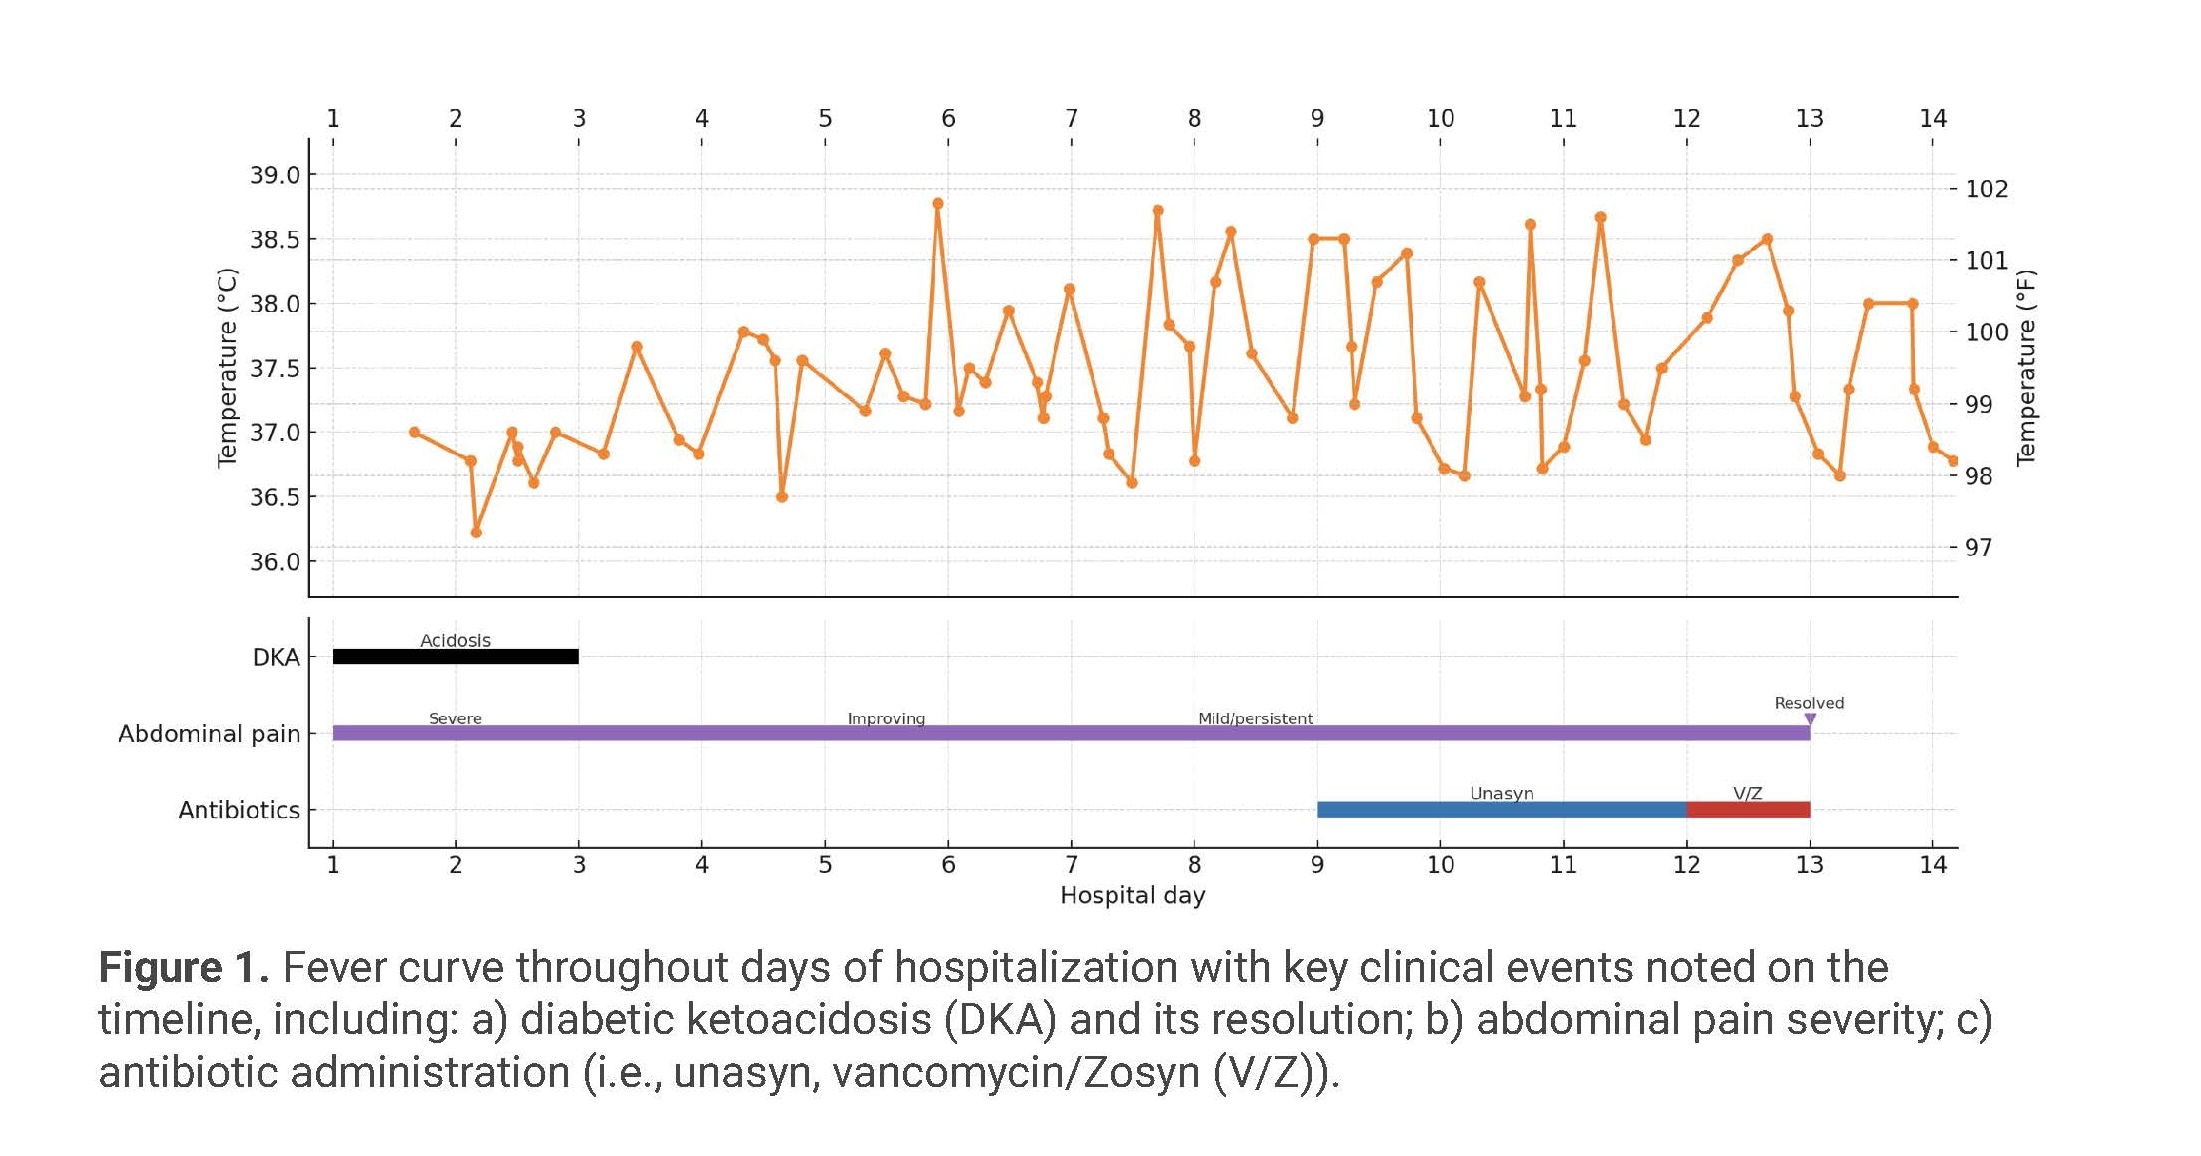
Case Presentation: A 33-year-old male with no medical history presented with severe epigastric pain radiating to the back. He was diagnosed with acute interstitial edematous pancreatitis secondary to hypertriglyceridemia (HTG) >4,425 mg/dL and new diabetic ketoacidosis (DKA) due to undiagnosed type II diabetes (GAD-65 antibodies negative). He received IV fluids, insulin, fenofibrate, and pain control. By hospital day 4, despite improving abdominal pain, resolving DKA, and decreasing triglycerides, he developed persistent fevers (Tmax 38.7°C), bandemia (20%), and elevated ESR/CRP (120 mm/hr; 34 mg/dL) without localizing symptoms.A comprehensive infectious evaluation – including blood cultures, urinalysis, respiratory and gastrointestinal pathogen testing, HIV, tuberculosis, and syphilis – was unrevealing. Ultrasound showed no DVT; echocardiogram was normal. Repeat imaging showed progression of interstitial pancreatitis without necrosis, fluid collection, or biliary obstruction. Chest imaging revealed only atelectasis and a small pleural effusion. Procalcitonin remained low (0.37 ng/mL day 8, 0.27 ng/mL day 10). With fevers persisting through day 12, empiric antibiotics for potential hospital-acquired pneumonia were trialed but discontinued when symptoms and the fever curve remained unchanged. He remained hemodynamically stable and was discharged on day 14, with persistent fever attributed to sterile pancreatic inflammation.
Discussion: The triad of DKA, severe HTG, and acute pancreatitis is an uncommon initial presentation of type II diabetes. It carries a higher risk of inpatient mortality, but the central challenge in this case was persistent fever and SIRS despite improving pancreatitis (1,2). Early fever in acute pancreatitis is often sterile within the first week; persistence typically raises concern for infected necrosis or extra-pancreatic infection (3,4). HTG-induced pancreatitis can produce a heightened inflammatory response and disease severity (5). Although fever duration correlates with disease severity in acute pancreatitis, available data do not define thresholds that guide management (4). Prior studies demonstrate that procalcitonin has strong diagnostic accuracy for ruling out infected pancreatic necrosis when imaging is equivocal, while CRP alone lacks specificity (6,7).In this case, repeat imaging showed no necrosis or fluid collection, low procalcitonin supported a noninfectious etiology, and the absence of clinical deterioration with an unchanged fever curve despite antibiotics argued against occult infection. Integrating biomarkers, imaging, and clinical stability supported discontinuation of antibiotics and avoidance of premature closure, highlighting the diagnostic difficulty of persistent fever in HTG pancreatitis and the importance of structured inpatient reasoning. Further data on fever duration in such cases may help prevent delayed discharge and unnecessary hospitalization.
Conclusions: This challenging and unusual case demonstrates that persistent fever after the first week in acute pancreatitis does not always signify infection or pancreatitis complications. When imaging, biomarkers, and clinical stability align, sterile SIRS should remain high on the differential. A disciplined approach that integrates validated markers such as procalcitonin and minimizes unnecessary antibiotic escalation strengthens antimicrobial stewardship and helps prevent overtreatment and delays in discharge.