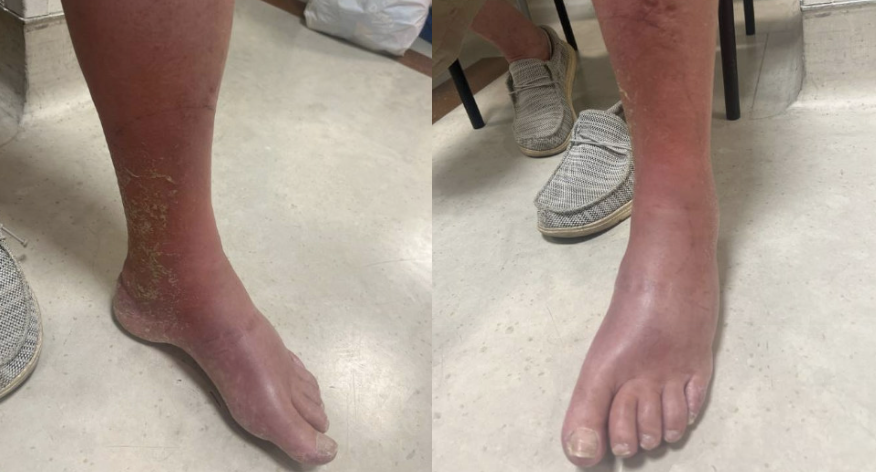
Case Presentation: A 79-year-old man with hyperlipidemia and depression presented to the ED with a suprapubic mass. After discharge with a nondiagnostic biopsy, he returned several months later with progressive vison loss, orbital cellulitis, and proptosis (Fig. 1). He also developed persistent left lower extremity swelling and erythema refractory to antibiotics (Fig. 2), along with weakness and bone pain. PET/CT demonstrated diffuse hypermetabolic activity in the long bones, perinephric regions, myocardium, and lymph nodes, consistent with his worsening bone pain. Multiple peripheral biopsies remained nondiagnostic, showing mixed lymphocytes, foamy histiocytes, and eosinophils, concerning for Kimura disease, xanthogranulomatous inflammation, or Langerhans cell histiocytosis. Bone marrow evaluation later revealed histiocytic aggregates, consistent with a histiocytic neoplasm. Given his multisystemic clinical picture and sequencing of MAP2K mutation and wild-type BRAF, he was diagnosed with Erdheim-Chester Disease (ECD). Targeted therapy with binimetinib/cobimetinib showed clinical and radiographic improvement but was complicated by a decline in LVEF, an established toxicity of MEK inhibition [1], and by orthostatic hypotension. Despite treatment interruptions due to malnutrition and pituitary dysfunction, the patient ultimately demonstrated improved functional status, resolution of orbital inflammation, and marked reduction in PET/CT activity. He remains hemodynamically stable on cobimetinib and pegylated interferon.
Discussion: ECD is a rare, multi-system non-Langerhans cell histiocytosis characterized by the infiltration of foamy histiocytes into skeletal and extra-skeletal tissues [2]. Although it most commonly affects middle-aged men, its presentations are heterogeneous, ranging from characteristic symmetric osteosclerosis of the long bones to involvement of the cardiovascular, neurologic, and endocrine systems [3]. This heterogeneous clinical picture contributed significantly to the patient’s delayed diagnosis; his constellation of symptoms initially appeared as unrelated, nonspecific findings, complicating early recognition. This case underscores the diagnostic challenges of ECD, where seemingly nonspecific imaging abnormalities and nondiagnostic peripheral biopsies, when considered together, may provide the critical clues needed to establish the diagnosis.
Conclusions: Ultimately, his course highlights both the therapeutic potential and the clinical complexity of managing ECD with targeted agents, especially in the setting of cardiac and systemic comorbidities. Given the rarity of ECD, early recognition of key symptoms and prompt evaluation remains critical to optimizing outcomes in this rare but increasingly recognized histiocytic neoplasm. Early recognition of atypical systemic patterns, timely involvement of subspecialists, and longitudinal coordination across inpatient and outpatient settings are essential to improving outcomes in ECD and similarly complex histiocytic neoplasms.